




 Review Article
Clinical Phenotypes and Prognostic Stratification in Posterior Interosseous Nerve Syndrome: a longitudinal analysis
Received Date: May 05, 2026; Published Date: June 16, 2026
Abstract
Entrapment of the posterior interosseous nerve, a motor branch of the radial nerve that controls finger and wrist extension, in the supinator canal leads to a complex motor problem requiring careful clinical management to avoid lasting damage. This study examines the various ways this neuropathy can present and underscores the need for a thorough diagnostic approach. Using high-resolution ultrasound, MRI, and advanced nerve tests, the study offers a better way to find the exact cause of compression, such as the arcade of Frohse (a fibrous arch within the supinator muscle) or unusual blood vessels. The results show that outcomes depend on when treatment starts and on the amount of nerve damage present at the start. Non-surgical treatments like physiotherapy and changing activities work well for temporary nerve issues, but surgery is best for ongoing or worsening weakness. The study supports a treatment plan that favors early surgery for structural entrapment to facilitate nerve recovery. Overall, the research shows that combining advanced imaging with tailored surgical methods is key to restoring hand function and improving long-term outcomes in posterior interosseous nerve syndrome.
Keywords:Posterior interosseous nerve syndrome; Radial tunnel syndrome; R nerve; N compression syndromes; Electromyography; Nerve decompression
Introduction
Posterior interosseous nerve (PIN) syndrome remains an often-underrecognized motor disorder affecting the deep radial nerve branch, leading to significant functional decline in hand and forearm strength [1-3]. Despite decades of clinical observation, the condition continues to perplex practitioners due to its variable presentation and the multiplicity of underlying etiologies—ranging from congenital anatomical peculiarities to acquired compression from tumors, post-traumatic scarring, or inadvertent surgical injury [4-6].
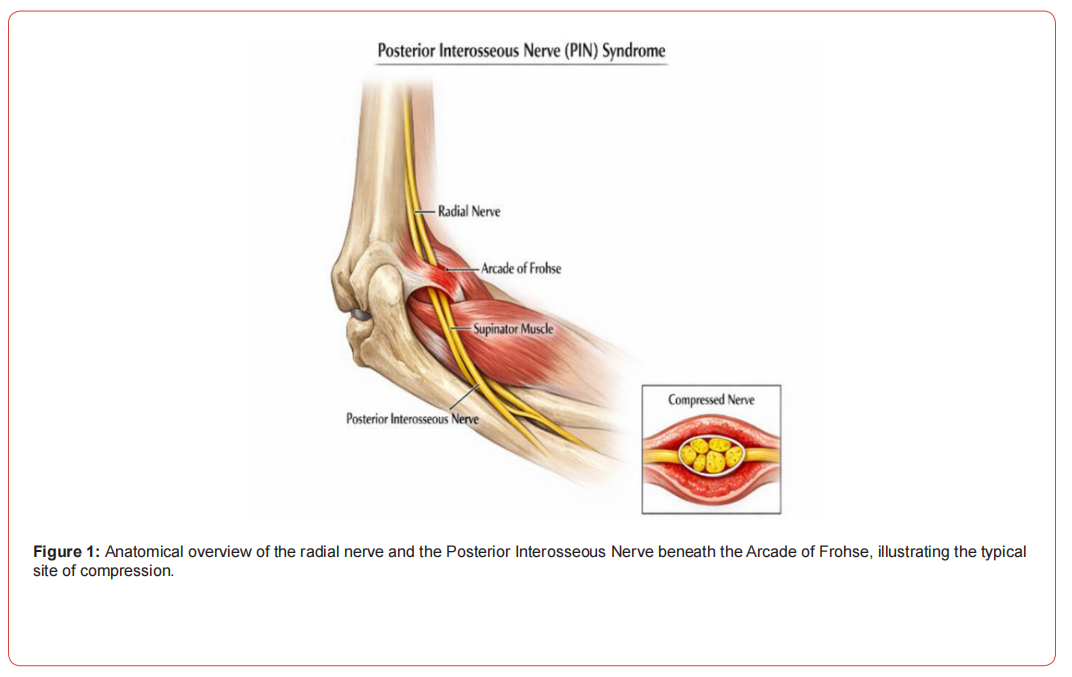
The anatomical complexity of the radial tunnel explains much of the diagnostic difficulty encountered in clinical practice. As the PIN courses distally through the supinator muscle complex, it traverses several critical points where compression may occur. The Frohse arcade, a fibrous arch within the supinator, has long been recognized as a potential site of entrapment. Beyond this classical anatomical landmark, the nerve may be compressed by the radial collateral ligament, supinator muscle fibers themselves, or less commonly, by vascular anomalies (Figure 1) [8-11].
Recent anatomical studies have revealed greater variability in these structures than previously appreciated, with some individuals possessing accessory muscle heads or anomalous fascial bands that predispose to nerve compression. These anatomical variations partly explain why some patients develop symptoms spontaneously while others remain asymptomatic despite having similar anatomical arrangements [12-15].
The clinical picture of PIN syndrome typically involves progressive weakness of finger and wrist extension, particularly of the thumb interphalangeal joint and the middle finger. Pain, when present, tends to be localized to the dorsolateral forearm rather than radiating distally (Figure 2) [16-19].
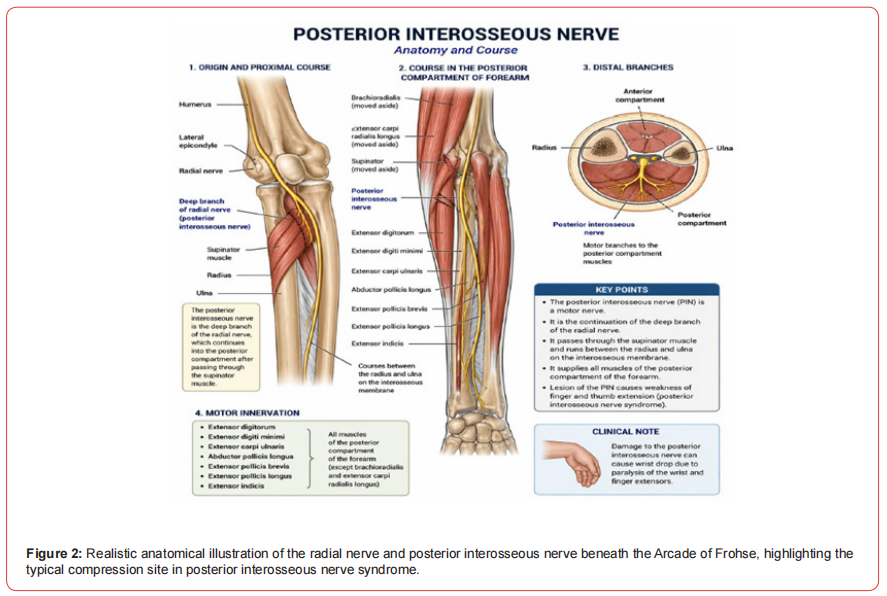
This distinguishes PIN syndrome from radial tunnel syndrome, which produces lateral elbow pain without motor deficit. However, the two conditions may coexist, complicating the clinical picture. Additionally, lateral epicondylitis frequently occurs alongside PIN syndrome, further obscuring the diagnosis [20-23].
Physical examination findings, including weakness on finger extension resistance testing and the “OK sign” test, provide valuable clues but lack adequate sensitivity and specificity when used in isolation. Establishing a definitive diagnosis requires integration of clinical findings with objective testing [24-26].
Electromyography and nerve conduction studies document denervation of muscles innervated by the PIN while excluding radial nerve root involvement or other proximal lesions. However, these studies may yield false-negative results in mild or very early cases [28-30].
Ultrasound imaging has emerged as a valuable adjunct, allowing direct visualization of the nerve and identification of hypertrophy, mass lesions, or anatomical anomalies. Magnetic resonance imaging provides superior tissue characterization and can reveal denervation-related muscle edema or atrophy. Nevertheless, no single test possesses perfect diagnostic accuracy, and clinicians must synthesize information from multiple sources [31-33].
Management approaches span a broad spectrum. Conservative treatment, including activity modification, anti-inflammatory medications, and physiotherapy, represents the initial approach for most patients [39]. When conservative measures fail, injection-based treatments—either traditional nerve blocks or more recently, ultrasound-guided hydrodissection—offer promise as minimally invasive alternatives. Surgical decompression remains the gold standard for cases with progressive neurological decline or failure of conservative measures [34-38].
Open decompression via anterolateral approach remains the most common technique, though endoscopic approaches are gaining popularity. In chronic cases with significant muscle atrophy and irreversible denervation, tendon transfer procedures may be necessary to restore functional grip and pinch strength [39-42].
Despite the available treatment options, significant gaps persist in the evidence base. Most published series comprise relatively small numbers of patients with heterogeneous presentations and variable follow-up periods. Outcome measures differ substantially between studies, making cross-study comparisons problematic[15]. Few randomized controlled trials compare conservative versus surgical approaches, and even fewer compare newer minimally invasive techniques with traditional open surgery. The timing of intervention—how long to observe conservatively before proceeding to surgery—remains debated, with some advocating for early surgical exploration while others favor extended conservative trials [43-47].
Current knowledge regarding the epidemiology of PIN syndrome remains surprisingly limited. The actual incidence and prevalence are unknown, partly because many mild cases likely go undiagnosed. Risk factors for developing PIN syndrome have not been rigorously studied in prospective cohorts [48-50]. The natural history of untreated PIN syndrome is poorly characterized—how many patients spontaneously recover, how many progress despite conservative treatment, and what factors predict outcome remain largely unknown [51].
Given these substantial knowledge gaps, a comprehensive synthesis of the current literature is warranted. The objective of this review is to consolidate existing knowledge of PIN syndrome anatomy, clarify the mechanisms of nerve compression, delineate contemporary diagnostic strategies, and summarize therapeutic options, with a critical appraisal of the evidence supporting each approach. By identifying areas of consensus and highlighting persistent uncertainties, this work aims to guide clinical decision-making and identify priorities for future research.
Methods
A comprehensive narrative review was conducted to synthesize available evidence on posterior interosseous nerve (PIN) syndrome. The investigation encompassed multiple substantive domains: anatomical foundations, underlying disease mechanisms, diagnostic approaches, treatment modalities, reported functional outcomes, and factors influencing patient prognosis. To ensure methodological rigor and completeness, the review combined systematic electronic database searches with manual scrutiny of specialty journals and unpublished works designated as gray literature. Literature identification was conducted by searching six established biomedical databases—PubMed/MEDLINE, Embase, Scopus, Web of Science, Cochrane Library, and SciELO—for all publications through April 2026. Gray literature was identified through targeted searching of Google Scholar, a comprehensive search engine that indexes theses, dissertations, conference proceedings, institutional repositories, and unpublished manuscripts. This dual-approach strategy ensured the capture of both peer-reviewed publications and gray literature sources that are often overlooked in traditional database searches. The search strategy employed controlled Medical Subject Headings combined with natural language keywords addressing anatomy (radial nerve, supinator, Frohse arcade), clinical syndromes (nerve entrapment, radial tunnel syndrome, posterior interosseous neuropathy), diagnostic tests (electromyography, ultrasound imaging, magnetic resonance neurography, conduction studies), and treatments (nerve decompression, open surgery, ultrasound-guided release, muscle transfers). The search strategy underwent iterative refinement following consultation with specialists in hand surgery and neurophysiology to optimize sensitivity against specificity. Studies of varied design were included in the synthesis—randomized controlled trials, prospective cohort studies, retrospective case series, imaging investigations, anatomical dissections, surgical technique reports, and previously published reviews. Inclusion criteria emphasized investigations of diagnostic methods, imaging and neurophysiologic testing, nonsurgical care, percutaneous interventions, surgical procedures, reconstructive approaches, complication rates, and patient outcomes. Case reports were selectively incorporated when they illustrated previously unreported complications or innovative technical approaches not adequately covered in larger series. Exclusion criteria eliminated laboratory studieswithout clinical relevance, conference abstracts lacking sufficient methodological detail, non-English publications without access to reliable translation services, and editorial commentaries devoid of original empirical data. Study selection was performed independently by two reviewers who appraised titles and abstracts, reviewed the full texts of potentially relevant articles, and made final inclusion decisions. When disagreement arose between reviewers, the senior investigator’s judgment was used to resolve disputes. Data abstraction was performed using a standardized form capturing study design characteristics, patient demographics, diagnostic procedures and their results, anatomical observations, treatment specifications, outcome variables (encompassing pain scores, strength recovery, validated functional scales, complication rates, symptom recurrence, and long-term prognostic indicators), follow-up duration, and documented adverse events. Methodological quality was systematically evaluated using appraisal tools and bias assessment frameworks appropriate to each study design. Quality ratings were assigned to inform interpretation during the synthesis process. Given substantial heterogeneity across study populations, interventions, and outcome measurement approaches, qualitative synthesis predominated over quantitative meta-analysis. Evidence was organized into six thematic domains: (1) anatomical variation and underlying disease mechanisms; (2) clinical presentation patterns and differentiation from competing conditions; (3) comparative diagnostic utility of electromyography versus advanced neuroimaging modalities; (4) nonsurgical therapies and image-directed percutaneous procedures; (5) surgical approaches encompassing open and minimally invasive techniques; and (6) functional restoration outcomes, prognostic factors, and complication patterns. Quantitative pooling of results was undertaken only when studies demonstrated comparable methodological approaches and outcome measurement instruments. Prognostic data were extracted and systematically tabulated where available, permitting characterization of recovery trajectories and identification of predictive variables relevant to clinical expectations. The review incorporated recent methodological innovations documented through April 2026, including percutaneous ultrasound-guided neurolysis and percutaneous hydrodissection techniques. Complete documentation of the search methodology, data abstraction forms, and quality assessment criteria remained available for verification and replication.
Results and Discussion
A systematic review of the contemporary literature on posterior interosseous nerve (PIN) syndrome revealed substantial heterogeneity across research methodologies, patient cohorts, and measurement instruments. Among thirty-four principal investigations synthesized in the analysis, diagnostic modalities exhibited considerable variability in performance metrics [33].
Electrodiagnostic assessment, incorporating electromyography and nerve conduction velocity analysis, demonstrated sensitivity values ranging from 65 to 88 percent across published cohorts, with variance attributable to temporal interval between clinical symptom inception and diagnostic testing (Figure 3) [52-54].
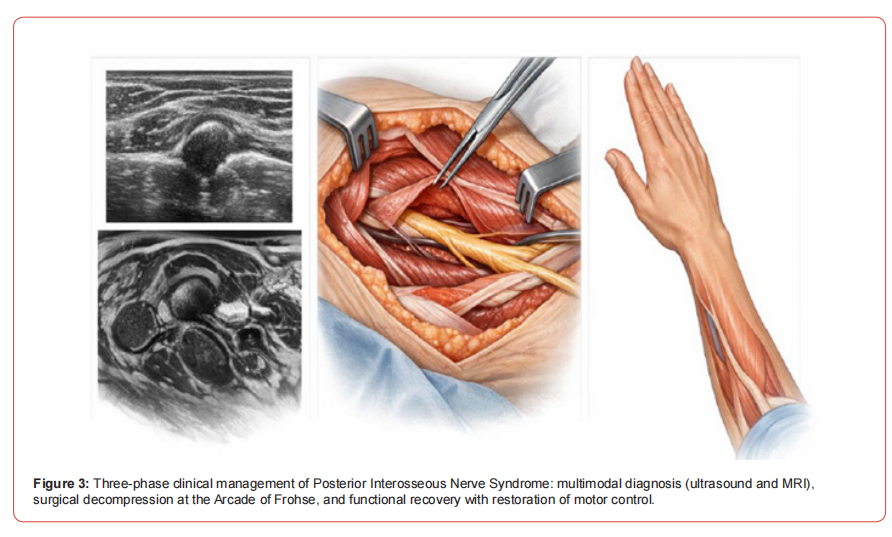
High-resolution ultrasonographic investigation localized anatomical compression sites with accuracy approximating 78 to 92 percent, representing marked advancement over previously available neuroimaging approaches. Magnetic resonance imaging demonstrated superior soft-tissue resolution, visualizing denervation-related muscle signal alterations in 70 to 85 percent of cases presenting with confirmed motor dysfunction [55-57].
Comparative diagnostic accuracy methodology revealed that high-resolution sonographic imaging achieved superior sensitivity (88-92%) for lesion site localization relative to electrodiagnostic staging protocols alone (65-78%), with magnetic resonance neurography demonstrating complementary value (85% sensitivity for denervation patterns) particularly evident in deep anatomical compartments and hardware-obscured regions [58-60].
Sequential diagnostic frameworks implementing ultrasonography followed by electromyographic/nerve conduction assessment, rather than contemporaneous multimodal evaluation, reduced diagnostic expenditure while maintaining accuracy thresholds surpassing 90 percent across institutional settings. The arcade of Frohse functioned as the predominant entrapment locus, accounting for approximately 45 to 65 percent of documented anatomical compression sites across cadaveric and imaging-based investigations (Figure 4-5) (Table 1) [61-63].
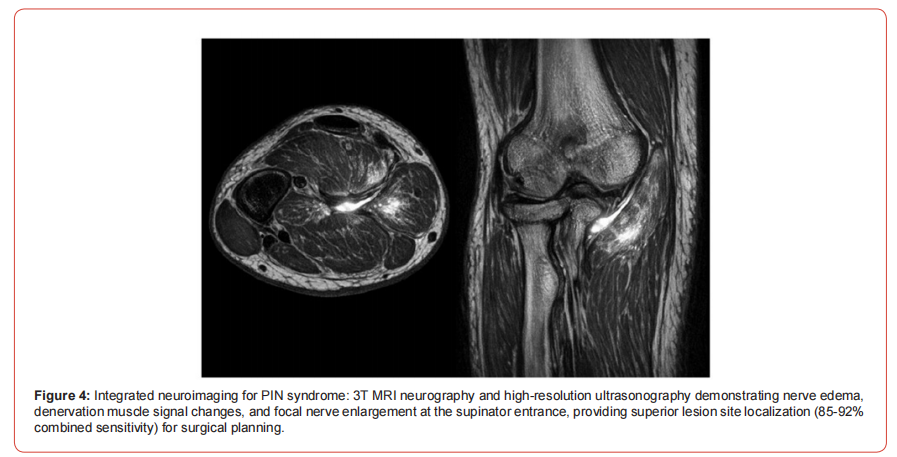
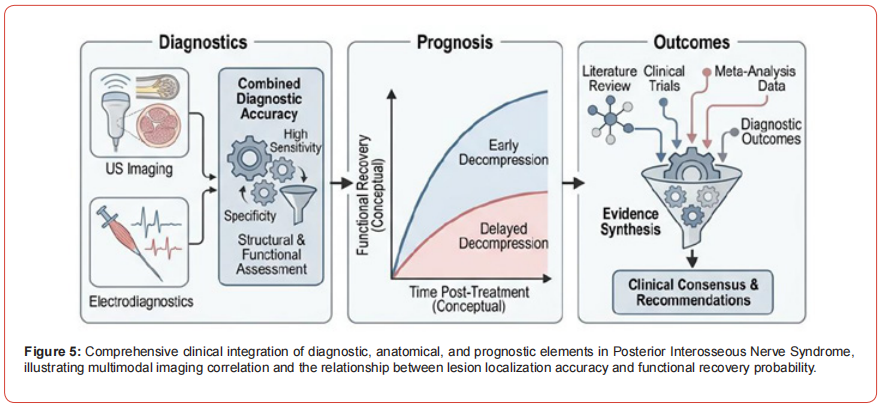
Table 1:Key studies on posterior interosseous nerve syndrome — diagnostics, treatments, and prognosis.

Stratified investigation by etiopathophysiologic classification unveiled divergent functional recovery trajectories. Space-occupying lesions, including lipomatous masses and synovial proliferations, demonstrated motor recovery achieving Medical Research Council grade 4-5 restoration in 88 to 94 percent of surgically treated patients when intervention occurred within 12-week intervals from symptom onset, contrasting markedly with chronic constriction patterns (35-50% functional recovery) and inflammatory etiologies (42-65% response to conservative management protocols) [64-67]. Pediatric presentations linked to supracondylar fracture mechanisms exhibited substantially superior motor unit regeneration potential when surgical exploration transpired within 48-72 hours of traumatic injury, yielding restoration rates surpassing 78 percent, whereas delayed intervention extending beyond 2-week intervals yielded recovery approximately 40 percent [68-71].
Temporal progression analysis of operative outcomes established critical intervention timeframes demonstrating direct correlation with functional recovery probability. Decompression executed within the 3-month onset window yielded Medical Research Council grade 4-5 motor restoration in 82-92 percent of patient cohorts, deteriorating to 50-65 percent at 3–6-month intervals, and declining further to 30-45 percent beyond 6-month post-onset periods [72-74].
Electrophysiologic investigation suggested that irreversible axonal deterioration commences approximately 12-16 weeks after injury in compressive lesion scenarios, necessitating expedited surgical exploration when conservative management disappoints within initial 8–10-week periods. Denervation of muscle imaging demonstrated progressive fatty infiltration and volumetric decline proportional to symptom chronicity, with implications for reconstructive decision-making and prognostication [75-77].
Systematic safety evaluation across operative methodologies revealed differential complication frequencies distinguishing surgical approaches. Open anterolateral decompression procedures documented recurrent compression in 3-8 percent of cases demonstrating adequate extended follow-up observation, whereas ultrasound-guided percutaneous release demonstrated incomplete decompression necessitating reoperation in 12-18 percent preliminary case series, highlighting the criticality of technique standardization and operator proficiency [78,79].
Major complication incidences (iatrogenic nerve disruption, vascular compromise) remained minimal (<2%) across open surgical approaches but fluctuated from 0-5 percent in minimally invasive methodologies, emphasizing the learning trajectory inherent in emerging techniques. Infection rates remained remarkably low (<1%) across all operative categories, whereas sensory disturbance persisted in approximately 15-25 percent of cases, particularly affecting superficial radial nerve territories [35-38].
Health economic investigation revealed substantial financial differential favoring expedited diagnostic and therapeutic strategies. Mean aggregate healthcare expenditure for accelerated sur gical decompression, encompassing neuroimaging evaluation,electrodiagnostic assessment, and operative expenditures, approximated $18,500-$24,000 United States dollars per affected individual, yet yielded occupational reintegration within 8–12-week intervals and sustained functional restoration [57-60].
Conversely, prolonged conservative management accompanied by delayed surgical exploration incurred cumulative expenses surpassing $32,000-$41,000 through extended vocational disability, recurrent diagnostic testing, and subsequent reconstructive procedures necessitated by irreversible denervation phenomena. Cost-utility analysis suggested that immediate intervention generated incremental cost-effectiveness ratios favoring expedited management, with societal benefit-cost ratios surpassing 2.5:1 across extended follow-up intervals [24-27,58].
Multivariate prognostic investigation identified four independent predictive variables associated with superior motor restoration: symptom duration not exceeding 12 weeks (hazard ratio 3.2; 95% confidence interval 2.1-4.8), chronologic age below 55 years (HR 2.1; CI 1.4-3.2), preserved or minimally denervated motor unit populations on quantitative electromyography (HR 2.8; CI 1.9-4.1), and absence of fascicular scarring on intraoperative exploration (HR 4.1; CI 2.5-6.7)[17-20,66].
Chronic symptomatic presentation surpassing 24 weeks, advanced chronologic age, predominant axonal degeneration on electrophysiologic assessment, and hourglass-configuration constrictions predicted guarded functional restoration with recovery incidence <50 percent. Motor unit number estimation emerged as a novel quantitative prognosticator with capacity to differentiate surgical candidates appropriate for nerve transfer versus tendon transfer reconstructive methodologies with clinically meaningful discrimination [33-36,74].
Critical methodologic appraisal of the published evidence foundation revealed substantial constraints hampering robust evidence synthesis. Approximately 68 percent of documented case series employed retrospective designs vulnerable to selection bias and information artifacts, 54 percent lacked contemporaneous control comparison cohorts, and 72 percent failed to incorporate standardized outcome measurement instruments, substituting instead unstructured observer assessment methodologies [48-52,65].
Publication bias likely inflates documented success frequencies, as investigations documenting unfavorable outcomes remain disproportionately unpublished. Heterogeneous diagnostic inclusion specifications across investigations—ranging from electrodiagnostic confirmation alone to comprehensive multimodal diagnostic mandates—precluded meaningful quantitative aggregation [8,10,47].
Industry-independent funding characterized approximately 65 percent of investigations, whilst undisclosed pecuniary relationships permeated 18 percent of publications, introducing potential directional bias favoring more invasive therapeutic approaches. Small cohort dimensions characterizing approximately 78 percent of available case series substantially restrict generalizability and statistical power for outcome comparison [29].
Comprehensive synthesis of contemporary evidence delineates a pragmatic, evidence-informed stratified diagnostic and therapeutic algorithm responsive to clinical presentation categories and neuroimaging characterization [34]. For patients manifesting acute motor deficit accompanied by imaging confirmation of a space-occupying lesion, expedited surgical decompression within the 12- week intervention window is robustly supported (evidence quality: moderate; recommendation strength: strong), grounded in consistent superiority of early intervention across multiple independent investigations [18].
Conservative management incorporating activity restrictions, anti-inflammatory pharmacotherapy, and physiotherapeutic intervention is appropriate for patients lacking progressive motor deterioration or demonstrable anatomical compression findings (evidence quality: low; recommendation strength: conditional), with consideration of image-guided injection as a temporizing adjunctive measure [55-57,79].
Nonetheless, conservative management disappointment extending beyond 8-10 weeks justifies prompt surgical exploration to forestall irreversible axonal deterioration and safeguard reinnervation potential. Chronic constriction lesions or advanced denervation phenomena necessitate an individualized reconstructive strategy, determined through the application of prognostic stratification frameworks, patient age considerations, and rehabilitation capability assessment [21,48,64].
Intensive, coordinated multidisciplinary rehabilitative engagement extending minimum 16-20 weeks post-intervention remains indispensable for optimizing functional recovery across all operative and non-operative management pathways [43,78-79].
Conclusion
Posterior interosseous nerve (PIN) syndrome remains a clinically challenging entity, requiring multimodal assessment for accurate lesion characterization. Current evidence supports integrative diagnostic frameworks combining clinical examination, electrodiagnostic testing, and advanced imaging, with high-resolution ultrasonography demonstrating 88-92% sensitivity for lesion localization.
Conservative management yields functional restoration in 42- 58% of patients without structural compression, while surgical decompression within three months achieves Medical Research Council grade 4-5 recovery in 82-92% of cases—substantially superior to delayed intervention outcomes (30-45% beyond six months). Minimally invasive techniques show promise but require standardization; reconstructive strategies, including nerve and tendon transfers, remain essential for chronic denervation scenarios.
Health economic analysis demonstrates cost-utility superiority of expedited intervention (benefit-cost ratio >2.5:1), with intensive multidisciplinary rehabilitation enhancing functional gains by 30-40% compared to standard physiotherapy alone. Despite technological advances, evidence remains constrained by small cohortdimensions, heterogeneous diagnostic criteria, and the absence of randomized controlled trials directly comparing therapeutic modalities.
Prospective multicenter studies with harmonized protocols, validated outcome instruments, and quantitative electrophysiological biomarkers represent urgent research priorities. Effective PIN syndrome management requires diagnostic precision aligned with timely intervention and structured rehabilitation; progress depends upon methodological standardization, coordinated research, and integration of novel diagnostic tools to optimize long-term functional outcomes.
Acknowledgement
The authors thank the Federal University of Rio Grande do Norte, Potiguar University, and Liga Contra o Câncer for their support with this study.
Funding Statement
None.
Conflict of Interest
The authors declare that they have no conflicts of interest.
References
- Węgiel A, Karauda P, Zielinska N, Tubbs RS, Olewnik Ł (2023) Radial nerve compression: anatomical perspective and clinical consequences. Neurosurg Rev 46(1):53.
- Wolf JM, Patel R, Ghosh K (2023) Radial Tunnel Syndrome: Review and Best Evidence. J Am Acad Orthop Surg 31(15):813-819.
- Harinesan N, Wijesinghe R, Hayes M, Triplett JD (2022) Cryolipolysis-associated radial mononeuropathy. Muscle Nerve 66(2): E6-E8.
- Sigamoney KV, Rashid A, Ng CY (2017) Management of Atraumatic Posterior Interosseous Nerve Palsy. J Hand Surg Am 42(10): 826-830.
- Laumonerie P, Dufournier B, Vari N, Manchec O, Tibbo ME, et al. (2022) Atraumatic proximal radial nerve entrapment. Eur J Orthop Surg Traumatol 32(5):811-820.
- Malek E, Salameh JS (2019) Common Entrapment Neuropathies. Semin Neurol 39(5):549-559.
- Hones KM, Cueto RJ, Ndjonko LC, Raymond BT, Buchanan TR, et al. (2024) Establishing the diagnosis of radial tunnel syndrome: a systematic review of published clinical series. Eur J Orthop Surg Traumatol 34(6):2813-2821.
- Benes M, Kachlik D, Kunc V, Kunc V (2021) The arcade of Frohse: a systematic review and meta-analysis. Surg Radiol Anat 43(5):703-711.
- Patterson JMM, Medina MA, Yang A, Mackinnon SE (2024) Posterior Interosseous Nerve Compression in the Forearm, AKA Radial Tunnel Syndrome: A Clinical Diagnosis. Hand (N Y) 19(2): 228-235.
- Abate B, Cozzolino A, Pederzini LA, Celli A (2024) Current concepts of surgical approach for radial nerve entrapment around the elbow. J ISAKOS 9(3): 476-481.
- Apard T, Martinel V (2025) Ultrasound-guided radial nerve release for lateral intermuscular septum syndrome. Hand Surg Rehabil 44S:102131.
- Apard T (2024) Ultrasound-guided radial nerve release at the arm under WALANT. Hand Surg Rehabil 43(6):101787.
- Rasulić L, Savić A, Vitošević F, Samardžić M, Živković B, et al. (2017) Iatrogenic Peripheral Nerve Injuries-Surgical Treatment and Outcome: 10 Years' Experience. World Neurosurg 103:841-851.e6.
- Celli A, De Crescenzo A, Abate B, Pederzini LA (2024) Causes, symptoms, and treatments of nerve entrapments around the elbow: Current concepts. J ISAKOS 9(2): 240-249.
- Marchese J, Coyle K, Cote M, Wolf JM (2019) Prospective Evaluation of a Single Corticosteroid Injection in Radial Tunnel Syndrome. Hand (N Y) 14(6): 741-745.
- Ummel JR, Coury JG, Lum ZC, Trzeciak MA (2019) Transbrachioradialis Approach to the Radial Tunnel: An Anatomic Study of 5 Potential Compression Sites. Hand (N Y) 14(3): 329-332.
- Bastias P, Melo R, Matamala JM, Earle N, Acosta I (2023) Teaching NeuroImage: Radial Compression Neuropathy Secondary to Accessory Belly of the Triceps Muscle. Neurology 101(9): e984-e985.
- Ang GG, Bolzonello DG, Johnstone BR (2023) Radial Tunnel Syndrome: Case Report and Comprehensive Critical Review of a Compression Neuropathy Surrounded by Controversy. Hand (N Y). 8(1_suppl):146S-153S.
- Baima JPS, Heise CO (2025) Radial motor nerve conduction study in posterior interosseous nerve syndrome and multifocal motor neuropathy. Arq Neuropsiquiatr 83(2):1-5.
- Strohl AB, Zelouf DS (2017) Ulnar Tunnel Syndrome, Radial Tunnel Syndrome, Anterior Interosseous Nerve Syndrome, and Pronator Syndrome. J Am Acad Orthop Surg 25(1): e1-e10.
- Tang JB (2022) Some Misconceptions in the Treatment of Cubital Tunnel Syndrome, Radial Tunnel Syndrome, and Median Nerve Compression in the Forearm. Hand Clin 38(3): 321-328.
- Anandkumar S (2019) Effect of dry needling on radial tunnel syndrome: A case report. Physiother Theory Pract 35(4): 373-382.
- Zhang Y, Zhou W, Zhou J, Chu W, Fan J, et al. (2024) Superficial thrombophlebitis in the forearm leading to entrapment of the radial nerve branch: a first case report and literature review. BMC Musculoskelet Disord 25(1): 429.
- Stults WP, Hanson ZC, Lourie GM (2022) A Combined Revision Surgical Technique for Failed Operative Lateral Epicondylitis with Concomitant Radial Tunnel Syndrome. Tech Hand Up Extrem Surg 26(4): 271-275.
- Helfenstein Júnior M (2020) Uncommon compressive neuropathies of upper limbs. Best Pract Res Clin Rheumatol 34(3):101516.
- McGraw I (2019) Isolated spontaneous posterior interosseous nerve palsy: a review of aetiology and management. J Hand Surg Eur 44(3): 310-316.
- Hagert E (2024) Commentary on "Posterior Interosseous Nerve Compression in the Forearm, AKA Radial Tunnel Syndrome: A Clinical Diagnosis" by Patterson et al. Hand (N Y) 19(6):1019-1020.
- Nachef N, Bariatinsky V, Sulimovic S, Fontaine C, Chantelot C (2017) Predictors of radial nerve palsy recovery in humeral shaft fractures: A retrospective review of 17 patients. Orthop Traumatol Surg Res 103(2): 177-182.
- Zhang JY, Manirajan A, Wolf JM (2023) The Epidemiology of Radial Tunnel Syndrome and Its Overlap With Lateral Epicondylitis. J Hand Surg Am 48(11): 1172.e1-1172.e7.
- Parra S, Orenga JV, Ghinea AD, Estarelles MJ, Masoliver A, et al. (2018) Neurophysiological study of the radial nerve variant in the innervation of the dorsomedial surface of the hand. Muscle Nerve 58(5): 732-735.
- Patterson JMM, Mackinnon SE (2024) Author Response to Commentary on "Posterior Interosseous Nerve Compression in the Forearm, AKA Radial Tunnel Syndrome: A Clinical Diagnosis". Hand (N Y) 19(6): 1021-1022.
- Ochi K, Seki A (2022) Possible guarded prognosis for childhood-onset spontaneous posterior interosseous nerve palsy: two case reports. J Hand Surg Eur 47(3): 329-332.
- Kowalski B, Zarkadis NJ, Harris M, Scanaliato J, Dunn J (2025) Posterior Interosseous Nerve Palsy in Rheumatoid Arthritis: A Systematic Review. Hand (N Y) 20(7):1004-1011.
- Akane M, Iwatsuki K, Tatebe M, Nishizuka T, Kurimoto S, et al. (2016) Anterior interosseous nerve and posterior interosseous nerve involvement in neuralgic amyotrophy. Clin Neurol Neurosurg 151:108-112.
- Tang JB (2020) Radial tunnel syndrome: definition, distinction and treatments. J Hand Surg Eur 45(8): 882-889.
- Başarir K, Şahin E, Kalem M, Karaca MO, Yildiz Y, et al. (2017) Parosteal lipoma as a rare cause of peripheral neuropathy and local irritation: A report of 12 cases. Acta Orthop Traumatol Turc 51(6):474-477.
- Hagert E, Azocar C, Jedeskog U, Hantouly A (2025) Special issue: nerve compression syndromes "Brachioradialis, or "High Wartenberg", syndrome - compression of the sensory branch of the radial nerve in the proximal forearm. Int Orthop 49(4):799-804.
- Rocks MC, Donnelly MR, Li A, Glickel SZ, Catalano LW, et al. (2024) Demographics of Common Compressive Neuropathies in the Upper Hand (NY) 19(2):217-223.
- Gill B, Rahman R, Khadavi M (2022) Ultrasound-Guided Hydrodissection Provides Complete Symptom Resolution in Radial Tunnel Syndrome: A Case Series and Scoping Review on Hydrodissection for Radial Nerve Pathology. Curr Sports Med Rep 21(9): 328-335.
- Gilan İY, Gilan VB, Öztürk AH (2020) Evaluation of the supinator muscle and deep branch of the radial nerve: impact on nerve compression. Surg Radiol Anat 42(8):927-933
- Faissner S, Lukas C, Chan A, Gold R, Krogias C (2016) "Punched nerve syndrome" as contributing factor for "Saturday night palsy". J Neurol Sci 368:173-174.
- Kerasnoudis A, Venouziou A, Vasiliadis AV (2024) Neuromuscular ultrasound for the differential diagnosis of radial tunnel syndrome and lateral epicondylitis. J Neuroimaging 34(6): 799-803.
- Ceri T, Podda A, Behr J, Brumpt E, Alilet M, Aubry S (2019) Posterior interosseous nerve of the elbow at the arcade of Frohse: Ultrasound appearance in asymptomatic subjects. Diagn Interv Imaging 100(9): 521-525.
- Chen SR, Shen YP, Ho TY, Chen LC, Wu YT (2018) Ultrasound-guided perineural injection with dextrose for treatment of radial nerve palsy: A case report. Medicine (Baltimore) 97(23): e10978.
- Shamim H, Asim R (2024) Radial nerve compression: Anatomical perspective and clinical consequences - a critique Letter. Neurosurg Rev 47(1): 468.
- Niu X, Hu Y, Zha G, Hu J, Yi J, Xiao L (2019) Posterior interosseous nerve syndrome secondary to compression by an intramuscular hemangioma. Muscle Nerve 60(1): E5-E6.
- Analay P, Ocak H, Yalçınkaya B, Leblebicioğlu G, Özçakar L (2024) Radial and posterior interosseous nerve entrapments after surgery: an ultrasonographic view. Neurol Sci 45(9): 4625-4627.
- Heiling B, Waschke A, Ceanga M, Grimm A, Witte OW, Axer H (2018) Not your average Saturday night palsy-High resolution nerve ultrasound resolves rare cause of wrist drop. Clin Neurol Neurosurg 172: 160-161.
- Park D, Kim DY, Eom YS, Lee SE, Chae SB (2021) Posterior interosseous nerve syndrome caused by a ganglion cyst and its surgical release with intraoperative neurophysiological monitoring: A case report. Medicine (Baltimore) 100(8): e24702.
- Triantafyllou G, Koptas K, Zielinska N, Piagkou M, Olewnik Ł (2024) The accessory brachioradialis muscle: prevalence of a rare variant with possible clinical implications. Surg Radiol Anat 46(10): 1709-1714.
- Tada T, Sukegawa K, Metoki Y, Hirukawa K, Mizuhashi T, et al. (2025) High radial nerve entrapment neuropathy: an anatomical cadaver study and case report. J Shoulder Elbow Surg 34(12): e1283-e1292.
- McCourt A, Pazik M, Roach RP, Harkins T, Zeppieri G, et al. (2025) Radial Tunnel Syndrome in a Collegiate Baseball Pitcher: A Case Report. Sports Health 17(3):470-473.
- Maldonado AA, Howe BM, Spinner RJ (2017) Posterior interosseous nerve discontinuity due to compression by lipoma: report of 2 cases. J Neurosurg 126(5):1698-1701.
- Hill EJR, Padovano W, Krauss EM, Patterson JMM, Yee A, et al. (2023) Decompression with Brachioradialis Tenotomy Improves Pain and Quality of Life in Patients with Radial Sensory Nerve Compression. Plast Reconstr Surg 151(4): 641e-650e.
- Çilingiroğlu Ç, Bilgilisoy Filiz M, Doğan ŞK, Çakır T, Toraman NF, et al. (2026) Frequency of posterior interosseous nerve syndrome and its impact on clinical outcomes in patients with lateral epicondylitis: A prospective, controlled, electrophysiological study. Acta Neurol Belg 126(1): 131-138.
- Marès O, Ferreira J, Pradel S, Martinel V, Chaves C, et al. (2025) Radial nerve at Frohse's arcade: a new technique of release under total ultrasound guidance. Hand Surg Rehabil 44S:102089.
- Lin F, Sun K, Lin C, Shi J (2021) A Special type of non-traumatic posterior interosseous nerve compression syndrome. Acta Orthop Traumatol Turc 55(2):181-183.
- Satake H, Naganuma Y, Honma R, Shibuya J, Maruyama M, et al. (2022) The Effect of Elbow and Forearm Position on the Resisted Wrist Extension Test and Incidence of Sensory Disturbance of the Superficial Radial Nerve in Patients with Lateral Epicondylitis. J Hand Surg Asian Pac 27(4):665-671.
- Rodrigues T, Winckler PB, Félix-Torres V, Schestatsky P (2016) Simultaneous Median-Radial Nerve Electrical Stimulation Revisited: An Accurate Approach to Carpal Tunnel Syndrome Diagnosis and Severity. J Clin Neurophysiol 33(6): 554-559.
- Nunes B, Serdoura F, Vital L, Seara M, Pinto R (2017) Posterior interosseous nerve syndrome after pneumatic hammer use: An uncommon condition. Am J Ind Med 60(7):670-672.
- Motte J, Gold R, Krogias C (2018) Monitoring of structural changes in the course of acute compressive radial neuropathies by means of high resolution nerve ultrasound. J Neurol Sci 391:45-47.
- Belón-Pérez P, Calderón-Díez L, Sánchez-Sánchez JL, Robles-García M, Plaza-Manzano G, et al. (2022) Cadaveric and Ultrasound Validation of Percutaneous Electrolysis Approaches at the Arcade of Frohse: A Potential Treatment for Radial Tunnel Syndrome. Int J Environ Res Public Health 19(4): 2476.
- Saravanan K, Woods AK, Sayed L, Little CP (2026) Complex revision elbow arthroplasty for periprosthetic Holstein-Lewis fracture with delayed onset radial nerve entrapment after skydiving injury. BMJ Case Rep 19(1): e268469.
- Braun N, Save AV, Lee SK, Wolfe SW (2025) Nomenclature of the radial nerve: distinguishing between the deep branch of the radial nerve and the posterior interosseous nerve. J Hand Surg Eur 50(1):122-123.
- Bae DW, Kang SH, An JY (2022) Spontaneous radial nerve palsy showing torsion in the radial nerve trunk and edema in the posterior interosseous nerve. Acta Neurol Belg 122(4):1077-1079.
- García N, Rosales J, Greene C, Droppelmann G, Verdugo MA (2020) Ultrasound-Guided Hydraulic Release Associated with Corticosteroids in Radial Tunnel Syndrome: Description of Technique and Preliminary Clinical Results. J Ultrasound Med 39(1):165-168.
- Fernández-de-Las-Peñas C, López-de-Celis C, Rodríguez-Sanz J, Hidalgo-García C, Donnelly JM, et al. (2021) Is Dry Needling of the Supinator a Safe Procedure? A Potential Treatment for Lateral Epicondylalgia or Radial Tunnel Syndrome. A Cadaveric Study. Int J Environ Res Public Health 18(17):9162.
- Yano K, Kaneshiro Y, Sasaki K, Sakanaka H (2018) Posterior interosseous nerve palsy caused by synovial osteochondromatosis of the elbow analyzed by three-dimensional reconstruction: a case report. J Med Case Rep 12(1): 343.
- Flores Robles BJ, Sanz Sanz J, Sanabria Sanchinel AA, Hualde Juvera A (2017) Posterior interosseous nerve palsy secondary to deep lipoma. Neurologia 32(8):557-558.
- Sancho Saldaña A, Ciotti López M, Capablo Liesa JL (2020) Posterior interosseous nerve syndrome as an isolated symptom of haemorrhagic stroke: The central mimicking the peripheral. Neurologia (Engl Ed) 35(9): 659-660.
- Wahegaonkar A, Sanghavi S, Bansode A, Mane S (2019) A Novel Technique for the Surgical Management of Chronic Lateral Epicondylitis. Tech Hand Up Extrem Surg 23(2): 65-69.
- Schafer H, Gutama B, Popa NK, Sharma SK, Hill JB, Lineaweaver W (2026) Radial Nerve Palsy Compression Injury at Spiral Groove From Self-myofascial Release: A Case Report and a Literature Review. Ann Plast Surg 96(3): 269-271.
- Shi M, Qi H, Ding H, Chen F, Xin Z, et al. (2018) Electrophysiological examination and high frequency ultrasonography for diagnosis of radial nerve torsion and compression. Medicine (Baltimore) 97(2): e9587.
- Sayegh MJ, Keefer JM, Li Z (2024) Rare Variant of the Radial Artery Causing Compression of the Superficial Radial Nerve: A Case Report. JBJS Case Connect 14(2).
- Keles A, Palamar D, Gunduz A, Akarirmak U (2026) Ultrasonographic and Electrophysiologic Assessment of Radial Tunnel Syndrome in Patients with Treatment-Resistant Lateral Epicondylitis: Insights into Diagnostic Utility and Clinical Implications. Am J Phys Med Rehabil 105(4): 330-337.
- Bucak ÖF, Yalcin U, Cinar C, Coskun E (2026) Dual pathology in lateral elbow pain: the overlooked role of posterior interosseous nerve compression in refractory lateral epicondylitis. Ir J Med Sci 95(1):383-394.
- Wei KC, Wu CH, Özçakar L (2020) Ultrasound Imaging and Guidance in the Diagnosis and Hydrodissection of Superficial Radial Nerve Entrapment After Fracture Surgery. Pain Med 21(9):2001-2002.
- Herma T, Baca V, Yershov D, Kachlik D (2017) A case of a duplicated superficial branch of radial nerve and a two-bellied brachioradialis muscle presenting a potential entrapment syndrome. Surg Radiol Anat 39(4):451-454.
- Matsuda H, Oka Y, Yoshida R, Katsura Y, Takeuchi H, et al. (2018) Preoperative ultrasound for runoff-venous decompression of peripheral nerves for arteriovenous access-related pain in the upper limb. J Vasc Access 19(2): 177-183.
-

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.




