




 Research Article
A Human-Centered Decision-Making Framework for Clinical Psychology-Based Drug Policy Evaluation: An MCDM Approach
Received Date:July 04, 2026; Published Date: July 13, 2026
Abstract
Drug control policies in West Africa often remain dominated by punitive and technocratic approaches that underrepresent lived experience, treatment access, stigma, and community participation. This study proposes a human-centered decision-making framework for evaluating drug policy alternatives from a clinical psychology and public health perspective. The framework links historical interpretivism, Actor-Network Theory (ANT), and co-design with a hybrid AHP-DEMATEL-ANP model. Historical interpretivism in-formed the identification of justice- and context-sensitive evaluation dimensions; ANT guided the mapping of interacting actors, institutions, treatment systems, laws, and social meanings; and co-design principles informed stakeholder-oriented criteria. Expert judgments were elicited using structured pairwise comparison and influence-assessment instruments. AHP was used to derive baseline weights, DEMATEL mapped causal relations among criteria, and ANP synthesized feedback effects into final policy priorities. Results show that humanistic values and participation/inclusivity carry the greatest decision weight and act as causal drivers of policy effectiveness and feasibility. Across both baseline and networked analyses, decriminalization with support systems and harmreduction approaches ranked above medicalization and prohibition-focused strategies. The findings should be interpreted as an expert-based decision-support model rather than direct evidence of policy impact. The study contributes an operational bridge between clinical-psychological humanism and multi-criteria policy evaluation, highlighting the need for drug policies that prioritize dignity, treatment access, historical jus-tice, and participatory governance.
Keywords:Drug control policy; relationist humanization; Historical Interpretivism; Actor-Network Theory (ANT); Co-design; Emergentist Principle; Analytic Hierarchy Process (AHP); The Decision-Making Trial and Evaluation Laboratory (DEMATEL); Analytic Network Process (ANP)
Introduction
Why must we move beyond the dominant positivist, technicist, and substantialist paradigms in public health policy? The answer is clear: despite decades of global intervention, public health challenges in West Africa persist, with policies failing to address the deep-rooted social, cultural, and human dimensions of health and disease [1,2]. These conventional approaches often treat health crises as isolated medical problems and rely on quantifiable metrics, technical fixes, and top-down enforcement, neglecting the lived experiences, values, and relational networks that shape health outcomes. This enduring failure demands a radical rethinking: not merely a critique, but the construction of an alternative methodological foundation for health policy analysis.
When scientific rationality reaches its limits in understanding complex human phenomena, humanism offers more than ethical reflection, it provides a rigorous epistemological alternative. We clarify that our use of human-ism diverges from the traditional conception of medical humanism, which focuses solely on clinical empathy. Instead, we advocate for humanism as a methodology, a mode of inquiry that centers meaning, interpretation, and valueladen sense-making in public health policy formation. There is a call for the humanities to reshape social science that remains urgently relevant, especially as recent studies continue to reproduce insights within positivist, technicist, and substantialist frameworks [3,4]. In contrast, we promote a form of public health thinking that prioritizes reading between the lines, attending to context, history, and socio-cultural nuance over purely experimental or quantitative argumentation.
To this end, this paper introduces a novel methodological framework: an emergentist model that synthesizes three distinct but complementary traditions, historical interpretivism, Actor- Network Theory (ANT), and co-design, into a unified approach we term relationist humanization. This model is not a mere combination of methods but a generative integration designed to produce deeper, more humane, and more actionable insights into public health policy in West Africa. The first pillar of our emergentist model is historical interpretivism, which treats public health policy as historically constructed through cultural meanings, moral judgments, and ideological struggles. Public health historians such as Berridge [5] have long demonstrated that health systems and policies are not neutral or inevitable but emerge from contested socio-political processes. Their work aligns with Dvora Yanow’s interpretivist agenda in policy studies [6], which insists on the centrality of tacit knowledge, context, and symbolic interpretation. As Berridge [5] argues, historians must spiritually illuminate the formation of health systems, not just describe them, but reveal their psycho-sociological foundations. We embrace this view: interpretive policy analysis is not about objectivity but about understanding how health crises are rationalized through culturally conditioned sensibilities.
Yet, while historical interpretivism provides depth, it often lacks tools to map the dynamic networks through which policies are enacted. This is where relationism becomes essential. The relationship between humanity and health systems is complex and entangled [7]. Some studies explore the moral implications of public health decisions, while Bradford [8] trace health policies’ role in socio-political contexts, such as colonialism and imperialism. Public health movements, such as those in response to disease outbreaks, are globally connected, deeply tied to national identities [9]. Kim [10] further reveals how geopolitics shapes regional health policies.
Despite these contributions, public health historians have not fully systematized a framework that integrates relationism into humanistic policy analysis. Without such a structure, the translation of historical insight into participatory governance remains fragmented. The novelty of this paper lies precisely in the integration of these three strands into a single, coherent methodology. The emergentist model does not simply apply ANT or co-design to historical analysis; it fuses them with historical interpretivism to generate new forms of understanding. By grounding co-design in Latourian philosophy, we enable a historically informed, relationally attuned, and ethically engaged approach to policy development, one that marks the meaning-making of public health crises with what we call a relationist asterisk: a methodological signature that highlights the psychologistic, collaborative, and networked nature of human agency.
ANT is conceptually useful to optimize healthcare interventions by dint of what we could only describe as relationist humanism because it offers “a people-centered perspective” from which interactions, partnerships and interprofessional collaborations are appraised to develop the optimization-focused integrated healthcare [11]. With references to these comments and the theorization of ANT-history propagated by Durepos [12], we could make a judgment on how there are at least three benefits for us to utilize ANT as a method for the historical interpretation of drug control policy, especially when humanist insights from opium history could be said to have resulted from different kinds of relationships. First, Latourian relationism is either a sensibility, an assumption [13], a contention or a speculation (as in the theory of actor-network) which, at the formalist level, would turn policy analysis and, by implication. This is because all these buzzwords mentioned above for the identification of ANT show the extent to which formality of Latourian relationism is determined by spiritualist inferences of alignments of interests and thinking [14] that are typical of value-related and interpretive humanities. One simply would not see the uses of humanist (and therefore spirituality-filled) lexicons like post-post-postmodernism, brainin- a-vat, or matters of concern [15]in the framings of naturalist, technicist and positivist sciences. A philosophical underpinning of deduction-based and psychologistic humanism, which would simply be in-compatible with STEM-oriented thinking, could be observed in [15] argument formulation when he sought unity between theorization and abstract concepts such as fair position [15] or infra-language. Drawing on the philosophy of formalization, the Latourian relationism could then be regarded as having the power to completely transform the historical-interpretive articulations of drug control policy into an expression of geisteswissenschaften when the reasoning form of ANT itself is characterized by an inferential mode of argumentation. All in all, similar to how [16] has compared ANT with ethnography, historical-interpretive scholars of drug control policy might benefit from the recognition that a Latourian history of opium displays interpretive humanism so as to turn policymakers into the ethnographer of narcotic regulations by conforming to the deductive formality of Latour’s thinking.
The actual make-ups of ANT are intrinsically compatible with delineating the verstehen-centered examinations of collaborations, partnerships, interprofessional teamwork, and interactions in implementation of drug control policy, which would call for the active involvement of all actors (human and non-human alike), including healthcare professionals and substance misusers to have their interests and meaning aligned in a network-based reality of policy making [17,1]. This is especially relevant when the catchphrase nothing about us without us [1] now dominates the debates concerning drug control institutions. Having a wider engagement with the electorate [18] is a realist proclamation of relationism whereby all actors should be involved in the policy sphere to attend to the underlying dynamics of power exchanges for the successful remedying of the drug issue [19,11]. The phrase power exchanges imply alignments of interests, meanings and thinking [14] through which we see the relationist humanization of substance regulation as a result of how historical interpretivism (and all the humanist sensibilities it represents) enters the ANTbased reality of drug control.
To exemplify, we return to a narcotic history narrated by Empires of Vice. With reference to what ANT historiographers have debated like [12,16], we tell a twofold story for a “relationist-humanist application” of Kim’s reconstruction of opium recollections in policy studies of drug control. To start with, the Empires of Vice as an entity is no doubt a Latourian gathering in its own right. In particular, contrary to orthodox understandings, we have purposefully occupied a revisionist position to blend Latourian relationism with Kantian purity because of how flat ontology can sometimes be too extreme to handle problems like critical barbarism and emancipation [20]. As indicated by Callon [21], include translation, problematization, interessement, enrollment and mobilization in a very different light that is premised upon the dissolution of objects in subjects to emphasize the activeness of human agency in the historical-interpretive examinations of a humanist drug control policy. Such is the reason why we have not paid excessive attention to opium sciences in the above example of producing a relationist description for how we could use Empires of Vice to illuminate policymakers over a relationist management of drugs.
However, ANT as a methodology for doing substance control policy has shortcomings. In the first place, a quick inspection of existing literature is sufficient to reveal that ANT, under some circumstances, could be too abstract to be practicalized. Another issue of formulating ANT as the modus operandi for approaching drug regulations is Latour’s ontological and epistemological positions on dualism. Instead of welcoming the Kantian purity of thing/object division, the French theorist rejected Janus on the grounds of hybridist compositionism and flat ontology [20]. This arguably leads to criticisms of how ANT wrongfully reduces people to the status of thing [22], which prevents us from addressing emancipation under certain circumstances [20]. And in the case of substance regulations, this is particularly damaging because the positivist, technicist and substantialist studies which dominate discussions about drug control policy have been reinforcing instrumentalism due to the lack of systematic understandings on structural constraints [20,18]. Co-design seems to be perfect for upgrading the methodology of substance control policy analysis, the reason being that it is a practical conceptualization of relationism that remedies the abstractness of ANT. The focus of co-designing an enterprise is on the real people and real-life situations as espoused by some of the highly cited works [23]. Thus, per the use of codesign, we could adjust the historical-interpretive framework to better practicalize what Berridge [5] said about the past of opioids being able to offer an interpretive richness for approaching drug control policy. Parenthetically, because co-design is heavily oriented towards actual projects due to its practicality, our following discussions are more of an operating manual than a philosophy of methods.
Co-designing a regime of substance control not only upholds the principles of patient-centered care, but also, in the process of upholding these principles, ensures the eluding of drug regulations from instrumentalist mentality originating from that positivist, technicist and substantialist thinking [18]. With co-designers stressing the participatory principle [24], the historical-interpretive scholars of drug control policy would significantly benefit from utilizing co-design as a method that channels humanism of opium history into the verstehen-centered understanding of real-life situations, the know-how of which is comparable to what New Zealand has done to tailor its graduated driving licensing system for the families of Maori and Pacific Island cultural backgrounds [25].
As indicated by a recently published paper [23], co-design has a strong capability for self-renewal. The reasoning goes that, because everyone in-volved in a given co-designed project constantly engages in participatory actions, interplays among the stakeholders are reflexive enough to encourage continuous revisioning of perspectives. Furthermore, co-designing a policy framework for drug control that has an emphasis on historicalinterpretivism would engender a relationist humanization which, similar to what Kirk [26] and her colleagues have articulated, is sufficiently competent to surpass the confines of positivism, technicism and substantialism so as to ensure that we have the transcendental subjectivity to respond to sudden changes in reallife by means of self-renewal. Despite everything outlined above, there are challenges that prevent us from maximizing co-design’s effectiveness in the historical-interpretive surveys of drug control policy. Probably, the most significant issue that we would face is the lack of theoretical development. Unlike ANT, whose undergirding is sometimes too philosophical to be practicalized, codesign is often the other way around [23,27]. Accordingly, it is hard not to have an impression after reviewing existing literature that, in lieu of building academic authority from theorizations, codesigners articulate their ideas via actual projects. This leads to the contextualization of co-design in implementation science, which frequently adopts under-defined terminologies due to the possible absence of theory-focused framework buildings [28,26].
To epitomize, a co-designed interpretivist rationalization of opium history as a method for drug control policy is not reifiable in the absence of a humanist recognition of human subtleties [29,30,31]. Frankly, opium historians who functionalize co-design to articulate their ideas about reconsidering drug regulations would certainly encounter issues beyond their anticipations when engaging elderly patients in a mobility study, which has already proven how co-designers can sometimes be inadvertently loyal to technicist and managerial positions [28,32], not to mention that collaborating with addicts and drug specialists would require greater shrewdness for tacit hu-manism. Syvertsen [33] have demonstrated some of the subtleties that are typical of humanism and which would compel co-designers to adopt a way of reasoning that rightfully addresses the subjectivity of humanity.
Materials and Method
This study used an expert-based multi-criteria decision-making (MCDM) design in Figure 1, in order to evaluate and prioritize policy alternatives, leading to a humanized drug policy to evaluate four drug-policy alternatives: prohibition-focused policy, harmreduction policy, medicalization, and decriminalization with support systems. The empirical material consisted of structured expert judgments rather than patient-level clinical data. The MCDM procedure was designed to transform theoretically grounded and clinically relevant policy values into transparent decision weights, causal relation-ships, and alternative rankings [34,35].

Experts Sampling Procedure
Experts were purposively recruited because the study required informed judgment on drug policy, clinical psychology, public health, institutional governance, or community-based intervention. All expert participants (N=50) were recruited from West African public health institutions, including ministries of health, universities, and non-governmental organizations. Eligible participants were adults aged 20 years or above with professional, academic, or policy experience related to public health, clinical psychology, addiction services, drug-policy research, law, social work, or institutional decision-making [36-38]. Experts with no relevant policy, health, or social-service experience were excluded. Recruitment was conducted through professional networks, academic contacts, and policy/practitioner referrals between January 2026 and March 2026. Participation was voluntary and uncompensated [29,30].
Instrument Development
The questionnaire was developed in four stages. First, drugpolicy and public-health literature was reviewed to identify potential humanistic, psychological, participatory, effectiveness, and feasibility criteria [39,40]. Second, these criteria were grouped into four main dimensions: Humanistic Values, Policy Effectiveness, Participation and Inclusivity, and Feasibility and Sustainability. Third, eleven sub criteria were defined to make each dimension measurable, including dignity, historical justice, cultural sensitivity, harm re-duction, rehabilitation outcomes, stakeholder engagement, transparency, co-design practicality, resource requirements, institutional compatibility, and long-term adaptability. Fourth, the draft instrument was reviewed by five specialists for clarity, relevance, and redundancy before final administration.
Data Collection Procedure
The instrument contained three analytical sections. The AHP section asked experts to compare criteria and sub criteria pairwise using the Saaty 1–9 scale [34]. The DEMATEL section asked experts to score the direct in-fluence of each criterion on another criterion using a 0–4 scale, where 0 indicated no influence and 4 indicated very strong influence [35]. The alternative-evaluation section asked experts to assess the relative performance of the four policy alternatives against the criteria [41,42]. All questionnaires were checked for completeness and logical consistency. Inconsistent AHP responses with CR values above 0.10 were returned for verification or excluded according to the predefined rule [39].
Ethical Approval and Informed Consent
The study involved adult expert participants and collected professional judgments rather than patient records or clinical intervention data. Ethical approval/waiver was obtained from the Center for West African Studies of UESTC under approval number 20260012. All participants received an information sheet describing the study purpose, voluntary nature of participation, anonymity, confidentiality, and the right to withdraw before data aggregation. Written or electronic informed consent was obtained before participation. No personally identifiable responses are reported in the manuscript.
Aggregation and Analysis
Individual pairwise comparison matrices were aggregated using the geometric mean, which is appropriate for combining reciprocal expert judgments [34,35]. AHP was used to calculate local and global weights and to test judgment consistency through the consistency ratio. DEMATEL was then used to construct the normalized direct-relation matrix, total-relation matrix, prominence index, and relation index [43,44]. Positive relation values were interpreted as causal drivers, while negative values were interpreted as dependent effects. Finally, the ANP super matrix was constructed using AHP weights adjusted by DEMATEL interdependencies, and the limit super matrix was calculated until convergence [39]. A sensitivity analysis was conducted by varying the weights of the two leading criteria by ±10% to assess whether the final ranking of alternatives remained stable.
Table 1 presents the demographic information of the experts or participants involved in the study. It includes key attributes such as age group, gender, experience in policy design, and education level. Each attribute is broken down into relevant categories, showing the frequency of participants in each category along with the corresponding percentage. The age group of participants is categorized into four groups, with the majority falling between 31- 50 years (66% combined), suggesting a mature and experienced participant pool. The gender distribution indicates a majority of male participants (60%) compared to female participants (40%). The experience in policy de-sign shows a diverse range, with half of the participants having more than 10 years of experience, reflecting a well-experienced cohort. Lastly, the education level reveals that a significant majority (80%) of participants hold advanced degrees (Master’s or PhD), indicating a highly educated sample.
Table 1: Demographic Information of Experts/Participants.

Operationalization of ANT and Co-design
The core theoretical framework was operationalized in the survey instrument. Key ANT concepts, translation, enrolment, mobilization, and relationality, were operationalized as survey items measuring influence and collaboration among policy actors. Co-design principles were implemented by including participatory criteria and scenario-based decision tasks that reflected stakeholder engagement, historical justice, and treatment accessibility. Expert judgments were then processed through the AHP-DEMATEL-ANP workflow. Table 2 shows the theory-to-method operationalization of the study.
Table 2: Demographic Information of Experts/Participants.

Analytic Hierarchy Process (AHP)
AHP decomposes the problem into a hierarchy of goal, criteria, sub-criteria, and alternatives. Expert judgments are captured using pairwise comparisons on [45] 1–9 scale. The pairwise comparison matrix A is given by:
Integration of AHP, ANP, and DEMATEL
The results from AHP, ANP, and DEMATEL are integrated as follows:
a) AHP is used to generate baseline weights for criteria and subcriteria.
b) DEMATEL adjusts these weights by evaluating causal interdependencies.
c) ANP synthesizes these adjusted weights into a final networked super-matrix, which incorporates both AHP weights and DEMATEL causal relationships.
d) Final Decision: The synthesized priorities from the ANP model provide the final ranking of policy alternatives.
The final result is the prioritized list of policy alternatives based on the integrated methodology. While AHP-DEMATEL-ANP methods were inspired by general MCDM frameworks, all criteria and sub criteria were adapted specifically for the West African public health context. Additional context was informed by UNODC West Africa Drug Report [29] and the West Africa Commission on Drugs [30], ensuring that historical justice, participation, and treatment access were properly weighted.
Results
Results of AHP
Figure 2 illustrates the relative importance of the four main criteria in the decision hierarchy. Humanistic Values emerged as the most significant criterion, accounting for nearly half of the overall weight (0.473). This indicates that considerations such as dignity, justice, and cultural sensitivity dominate the evaluation of drug control policy. Participation & Inclusivity followed as the second most influential factor (0.284), reflecting the importance of stakeholder engagement and transparency in policy-making. Policy Effectiveness, while still relevant, carried a more modest weight (0.170), suggesting that outcomes are interpreted primarily through a humanistic lens rather than being narrowly defined by efficiency. Feasibility & Sustainability received the lowest weight (0.073), confirming that although practical concerns matter, they are subordinated to ethical and participatory dimensions. This distribution of weights demonstrates that the emergentist model systematically prioritizes human-centered and participatory values over purely managerial or technicist criteria.

Table 3 shows the weights of the four main criteria. Humanistic Values received the highest weight (0.473), followed by Participation & Inclusivity (0.284). Figure 3 provides a more granular view of the decision-making structure by showing the global weights of the eleven sub-criteria. SC1 Dignity (0.189) and SC2 Historical Justice (0.163) were the most heavily weighted, underscoring the centrality of protecting human dignity and acknowledging historical injustices in drug policy design. Other influential sub-criteria include SC6 Stakeholder Engagement (0.121), SC7 Transparency (0.094), and SC4 Harm Reduction (0.102), all of which highlight the participatory and rehabilitative orientation of the framework. In contrast, sub-criteria associated with feasibility, such as SC10 Institutional Compatibility (0.031), SC9 Resource Requirements (0.028), and SC11 Long-Term Adaptability (0.014), received considerably less emphasis. This pattern reinforces the conclusion that humanistic and participatory elements are not peripheral but rather the foundational drivers of effective policy, while technical feasibility is considered necessary but secondary.

Table 3: AHP Criteria Weights and Consistency.

Consistency ratio (CR) = 0.019(<0.1).
Table 4 reports the global weights of the sub-criteria. Dignity (0.189), Historical Justice (0.163), and Stakeholder Engagement (0.121) emerged as the most significant. Figure 4 presents the baseline ranking of the four policy alternatives derived from the AHP synthesis. Decriminalization with support systems (A4) achieved the highest priority (0.341), followed closely by harmreduction models (A2) with a weight of 0.319. Together, these approaches clearly out-perform prohibition (A1), which received the lowest weight (0.092). Medicalization (A3) occupied an intermediate position (0.248), reflecting its practical benefits but its relative lack of emphasis on participatory or justice-oriented considerations compared to decriminalization and harm reduction. This ranking confirms that prohibitionist approaches are not only less hu-manistic but also less effective when evaluated against the multidimensional criteria of the emergentist model. By contrast, alternatives that foreground dignity, justice, and participation align more closely with both humanistic imperatives and systemic effectiveness. The AHP baseline ranking of alternatives (Table 5) shows that A4 (Decriminalization + Support) and A2 (Harm- Reduction) outperform prohibitionist approaches.

Table 4: AHP Global Sub-criterion Weights (Top 11).

Results of DEMATEL
Figure 5 visualizes the causal interrelationships among the four main criteria using the DEMATEL method. Humanistic Values and Participation & Inclusivity are positioned in the positive region of the relation axis (D − R > 0), indicating that they function as causal drivers. This means that improvements in dignity, justice, and inclusivity will positively influence both effectiveness and feasibility. Policy Effectiveness lies close to the neutral line, reflecting its role as a responsive or dependent criterion, shaped by the causal forces of humanism and participation. Feasibility & Sustainability appears in the negative region (D−R < 0), confirming its status as an effect criterion that is largely determined by other drivers rather than exerting influence itself. This mapping aligns with Actor–Network Theory’s principle that systemic effectiveness is relationally produced and suggests that any durable reform in drug policy must begin with investments in humanistic and participatory foundations. The total relation matrix is reported in Table 6. Prominence–relation indices (Table 7) show that Humanistic Values and Participation & Inclusivity are causal drivers, while Effectiveness and Feasibility are influenced effects.

Table 5: AHP Baseline Priorities of Alternatives.

Table 6: DEMATEL Total Relation Matrix (T).
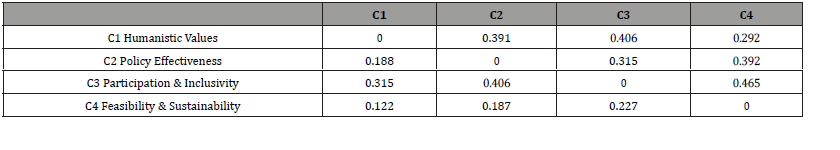
Table 7: DEMATEL Indices of Criteria.

Results of ANP+DEMATEL
The final comparison of AHP baseline vs ANP+DEMATEL priorities (Table 8) confirms the robustness of the ranking: humanistic and participatory approaches dominate, while prohibition is the least preferred.
Table 8: Final Comparison of Alternatives: AHP vs ANP+DEMATEL.

Discussion
The integration of AHP–ANP–DEMATEL in this study has provided a systematic means of operationalizing the emergentist methodology, translating the abstract principles of relationist humanization into a rigorous analytical framework. Each methodological component played a distinct but complementary role. AHP enabled the hierarchical structuring of humanistic and practical criteria, revealing the relative importance of values such as dignity, historical justice, and stakeholder participation. DEMATEL contributed by mapping the interdependencies among these criteria, offering a relationist perspective consistent with Actor–Network Theory (ANT), where criteria influence one another through networks of causality. ANP, finally, synthesized these interdependencies into a networked supermatrix that allowed for participatory complexity and feedback loops, aligning with the principles of co-design and collective decision-making. Together, these methods allowed us to bridge theory and practice in a way that pure qualitative or quantitative approaches alone could not achieve.
The results highlight a number of important findings. First, the AHP analysis established that Humanistic Values and Participation & Inclusivity are the most significant criteria, jointly accounting for more than 75% of the decision weight. This emphasizes that policy frameworks grounded in human dignity, historical justice, and participatory engagement are not simply normative ideals, but quantitatively dominant considerations in drug policy evaluation. Sub-criteria such as dignity, historical justice, stakeholde engagement, and harm reduction emerged as the most influential, reinforcing the argument that human-centered factors are essential to the legitimacy and effectiveness of drug control policies.
Second, the DEMATEL analysis revealed that Humanistic Values and Participation & Inclusivity function as causal drivers, exerting influence over Policy Effectiveness and Feasibility & Sustainability, which were more reactive or effect-based criteria. This relational mapping provides a significant theoretical insight: efforts to improve drug control policy cannot focus narrowly on efficiency or institutional feasibility alone, but must first cultivate humanistic and participatory foundations. In other words, dignity, justice, and inclusivity are preconditions for effectiveness, rather than optional or secondary considerations. This finding is consistent with the relationist logic of ANT, in which systemic outcomes are generated by the dynamic interplay of heterogeneous actors and values.
Third, the ANP+DEMATEL integration confirmed and reinforced the AHP baseline results. Even when accounting for interdependencies and feed-back loops, the ranking of alternatives remained robust: decriminalization with support systems (A4) and harm-reduction models (A2) consistently out-performed both medicalization (A3) and prohibition-focused strategies (A1). This consistency across methods demonstrates the stability of the conclusion that prohibitionist models are the least effective and least humanistic option. The networked analysis also slightly increased the weight of medicalization relative to prohibition, suggesting that while medicalization has practical merits, it remains secondary to approaches explicitly grounded in humanism and inclusivity.
These results provide a quantified basis for relationist humanization. By showing that policies prioritizing dignity, participation, and harm reduction consistently outperform prohibitionist models, the study challenges the long-standing reliance on punitive frameworks. Moreover, the integration of ANT and co-design into the analytical process ensures that these conclusions are not only theoretically coherent but also grounded in the realities of stake-holder interdependencies and participatory processes. While the quantitative results indicate a clear prioritization of humanistic and participatory policy alternatives, these findings are contingent upon expert judgments and should not be interpreted as direct causal evidence. The integration of ANT and co-design concepts into the empirical workflow allows the model to approximate relational and participatory dynamics, but future research should validate these results with actual policy outcomes in West Africa. This insertion strengthens the alignment between the conceptual framework and methodological implementation. The implications are clear: effective and sustainable drug policy must be human-centered, participatory, and historically informed. Prohibitionist approaches, rooted in technicist and positivist paradigms, fail to address the relational and cultural dynamics at the heart of substance use and regulation. By contrast, harmreductionist and decriminalization models are strengthened both theoretically and empirically by this study, offering a pathway for relationist humanization that bridges the gap between abstract humanist principles and concrete policy practice.
Conclusions
This study aims to advance a new approach to humanizing drug control policy by developing and operationalizing an emergentist methodology that integrates historical interpretivism, Actor- Network Theory (ANT), and co-design with the quantitative rigor of AHP, ANP, and DEMATEL. In doing so, it responds to the longstanding limitations of positivist, technicist, and managerialist approaches, which, despite dominating drug control since the declaration of the “war on drugs” in the 1970s, have consistently failed to produce satisfactory outcomes. The contribution of this research is twofold. Theoretically, it articulates the concept of relationist humanization, which emphasizes that policy effectiveness arises not from utilitarian logics or managerial control, but from the dynamic interplay of dignity, justice, inclusivity, and historical conscious-ness. By embedding these values into a hybrid MCDM framework, the study bridges the gap between abstract humanist principles and measurable decision criteria. Methodologically, the integration of AHP, ANP, and DEMATEL translates relationist insights into structured priorities, causal interdependencies, and networked synthesis, ensuring that humanistic considerations are not only acknowledged but quantified and incorporated into decision making.
The empirical results reinforce these theoretical claims. AHP analysis revealed that Humanistic Values and Participation & Inclusivity dominate the decision hierarchy, together accounting for more than three-quarters of the decision weight. DEMATEL further demonstrated that these two criteria act as causal drivers, shaping Policy Effectiveness and Feasibility & Sustainability. The ANP+DEMATEL synthesis confirmed the robustness of these findings, showing that decriminalization with support systems and harm-reduction models consistently outrank medicalization and prohibition focused approaches. These results provide a quantified foundation for the argument that prohibitionist strategies are the least aligned with humani-tic and participatory values, and therefore the least effective for addressing contemporary drug crises. The findings should be interpreted within the boundaries of an expert-based decision-support model. The study does not claim to measure actual policy outcomes, clinical treatment effectiveness, or community-level behavioral change. Instead, it shows how a structured panel of experts prioritized humanistic, participatory, effectiveness, and feasibility criteria when evaluating drug-policy alternatives. Because the model depends on expert judgments, future research should triangulate these results with interviews, focus groups, service-user perspectives, country-level policy data, and longitudinal evaluation of implemented drug-policy reforms. This limitation is especially important in West Africa, where national legal frameworks, treatment capacity, cultural meanings of substance use, and institutional resources vary across countries.
- Adam Holland, Alex Stevens, Magdalena Harris, Dan Lewer, Harry Sumnall, et al. (2023) Analysis of the uk government’s 10-year drugs strategy-a resource for practitioners and policymakers. Journal of Public Health 45(2): e215-e224.
- Margaret Pereira, John Scott, Amanda Beem (2020) Imaginary drug control and the failures of contemporary Australian drug policy. Contemporary Drug Problems 47(1): 29-42.
- Evan D Kharasch, J David Clark, Jerome M Adams (2022) Opioids and public health: The prescription opioid ecosystem and need for improved management. Anesthesiology 136(1): 10-30.
- Tse Yang Lim, Erin J Stringfellow, Celia A Stafford, Catherine DiGennaro, Jack B Homer, et al. (2022) Modeling the evolution of the us opioid crisis for national policy development. PNAS 119(23): e2115714119.
- Virginia Berridge (2008) History matters? history’s role in health policy making. Medical History 52(3): 311-326.
- Dvora Yanow (2007) Interpretation in policy analysis: On methods and practice. Critical Policy Studies 1(1): 110-122.
- Martin Plant (1999) Opium and the people: opiate use and drug control policy in nineteenth century england. BMJ 319(7202): 131.
- James Tharin Bradford (2019) Book reviews: Lucy inglis, milk of paradise: A history of opium. The Social History of Alcohol and Drugs 33(2): 347-349.
- Ryoko Yamamoto (2015) Reviewed work: Moral nation: Modern Japan and narcotics in global history. Asia: Local studies / global themes, 29 Miriam kingsberg. Pacific Affairs 88(2): 306-308.
- Diana S Kim (2020) Opium’s long shadow: From Asian revolt to global drug control. by steffenrimner. The Journal of Asian Studies 79(1): 263-264.
- Tadhg Ryan, Briga Hynes, Nuala Ryan, Aisling Finucane (2024) Investigating the use of actor-network theory in healthcare: a protocol for a systematic review. BMJ Open 14: e079951.
- Gabrielle Durepos, Albert J Mills (2011) Actor-network theory, anti-history and critical organizational historiography. Organization 19(6): 1-19.
- Barry Goodchild, Ed Ferrari (2024) Intermediaries and mediators: an actor-network understanding of online property platforms. Housing Studies 39(1): 102-123.
- G Walsham (1997) Actor-network theory and is research: Current status and future prospects. PP. 93-120.
- Bruno Latour (2004) Why has critique run out of steam? from matters of fact to matters of concern. Critical Inquiry 30(2): 225-248.
- Richie Nimmo (2011) Actor-network theory and methodology: Social research in a more-than-human world. Methodological Innovations 6(3): 108-119.
- Lianping Ti, Despina Tzemis, Jane A Buxton (2012) Engaging people who use drugs in policy and program development: A review of the literature. Substance Abuse Treatment Prevention Policy 7(47).
- Adam Holland (2020) An ethical analysis of uk drug policy as an example of a criminal justice approach to drugs: A commentary on the short film putting uk drug policy into focus. Harm Reduction Journal 17(97).
- Kathrin M Cresswell, Allison Worth, Aziz Sheikh (2010) Actor-network theory and its role in understanding the implementation of information technology developments in healthcare. BMC Medical Informatics and Decision Making 10(67): 1-11.
- Sven Modell (2020) For structure: A critical realist critique of the use of actor-network theory in critical accounting research. Accounting, Auditing & Accountability Journal 33(3): 621-640.
- Michel Callon (1984) Some elements of a sociology of translation: Domestication of the scallops and the fishermen of st brieuc bay. The Sociological Review 32(1): 196-233.
- Sharon Jackson (2015) Toward an analytical and methodological understanding of actor-network theory. Journal of Arts and Humanities 4(2): 29-44.
- William R Penuel, Anna-Ruth Allena, Kate Henson, Melissa Campanellaa, Rachel Patton, et al. (2022) Learning practical de-sign knowledge through co-designing storyline science curriculum units. Cognition and Instruction 40(1): 148-170.
- Colette Einfeld, Emma Blomkamp (2021) Nudge and co-design: complementary or contradictory approaches to policy innovation?. Policy Studies 43(5): 901-919.
- Emma Blomkamp (2018) The promise of co-design for public policy. Australian Journal of Public Administration 77(4): 729-743.
- Jeanette Kirk, Per Nilsen, Ove Andersen, Byron J. Powell, Tine Tjørnhøj-Thomsen, et al. (2022) Co-designing implementation strategies for the walk-cph intervention in Denmark aimed at increasing mobility in acutely hospitalized older patients: a qualitative analysis of selected strategies and their justifications. BMC Health Services Research 22(8): 1-16.
- Tamimu Mohammed Gadafi, Touray Musa, Nusrat Jahan, Abiola Azeez Azeez, Shahbub Alam (2025) Digital finance and structural trans-formation: Analyzing the influence of emerging financial indicators on retail sector expansion in China. iris journal of eco & buss manag 3 (3): 1-12.
- Jeanette Kirk, Thomas Bandholm, Ove Andersen, Rasmus Skov Husted, Per Nilsen, et al. (2021) Challenges in co-designing an intervention to increase mobility in older patients: a qualitative study. Journal of Health Organization and Management 35(9): 140-162.
- UNODC (2024) World drug report: West and central africa. United Nations Office on Drugs and Crime.
- West Africa Commission on Drugs (2022) A Public Health Approach to Drug Policy in West Africa. WACD, Accra.
- Mohammed Gadafi Tamimu, Shurong Zhao, Qianwen Xu, Jie Zhang (2026) Attention-based deep learning hybrid model for cash crop price forecasting: Evidence from global futures markets with implications for west africa. Applied Sciences 16(3): 1600.
- Tamimu Mohammed Gadafi, Ibrahim Osman Adam, Liu Yawen (2025) Modeling the financial drivers of China’s digital economy: Implications for sustainable growth. Strategic Business Research 1(1): 100013.
- Jennifer L Syvertsen, Spala Ohaga, Kawango Agot, Margarita Dimova, Andy Guise, et al. (2016) An ethnographic exploration of drug markets in Kisumu, Kenya. International Journal of Drug Policy 30: 82-90.
- TM Gadafi, L Decui, AP Darko (2025) Two-stage method-based on africa smart irrigation system assessment for willingness to pay: A case of Ghana northern region. Socio-Econ. Plan. Sci 102(2025): 102318.
- MG Tamimu, D Liang (2025) Sustainable mining development in Ghana: An integrated ahp-topsis-manhattan distance approach. Resour. Policy 110: 105757.
- Philp Kwaku Adjei, Tamimu Mohammed Gadafi, Zhiguang Qin, Lois Tweneboa Kodua (2025) Enhancing business intelligence through digital technologies: A deep learning approach for optimizing supply chain risk management in Ghana. Proceedings of the 2nd International Conference on Image Processing, Machine Learning, and Pattern Recognition.
- Philp Kwaku Adjei, Tamimu Mohammed Gadafi, Zhiguang Qin (2025) Enhancing business intelligence in Ghana through digital technologies: Optimizing management information sharing with cloud computing, big data, and ai. Proceedings of the 2025 International Conference on Artificial Intelligence and Digital Finance.
- Geoffrey Bentum-Micah, Shurong Zhao, Xiangxu Wang, Xiaoyan Cao, Tamimu Mohammed Gadafi, et al. (2026) Enhancing the global reach and pedagogical diversity of online Chinese language education across cultural contexts: Evidence from anglophone west africa. Acta psychologica 263: 106229.
- Mohammed Gadafi Tamimu, Shurong Zhao, Qianwen Xu, Jie Zhang, Xinyi Yin (2025) Pythagorean fuzzy-ahp (pf-ahp) approach for emerging new risk evaluation in China-west africa digital trade collaboration. Journal of Theoretical and Applied Electronic Commerce Research.
- Tamimu Mohammed Gadafi, Seini Toufic, Albert Awortwi Sagoe, Liang Decui, Hira Anwar (2025) Enhancing climate resilience through sustain-able agricultural intensification: An attention-based neural network for climate-smart agriculture modeling in Ghana. Proceedings of the 2025 International Conference on Smart Agriculture and Artificial Intelligence.
- Mohammed Gadafi Tamimu, Emmanuel Antwi, Sylvester Edmond Saidu, Daisy Ofosuhene, Boateng Edward Akwasi (2026) Sustainable ai-driven predictive modeling in agricultural supply chains: Ai, iot, and blockchain integration for climate adaptation in Ghana. Iris Journal of Economics & Business Management.
- Tamimu Mohammed Gadafi, Touray Musa (2025) An integrated fuzzy-bwm-topsis with chebyshev distance approach for risk evaluation in e-business cooperation. International Journal of Management and Fuzzy Systems.
- MG Tamimu, S Zhao, Y Wang, Y Yang, T Sun, et al. (2025) Fuzzy logic-bwm-based risk assessment for e-business cooperation in China-west africa digital trade: A path to sustainable business and policies. Glob. Econ. Res 1(2): 100014.
- S Zhao, MG Tamimu, A Luo, T Sun, Y Yang (2025) Hesitant fuzzy-bwm risk evaluation framework for e-business supply chain cooperation for China–west africa digital trade. J. Theor. Appl. Electron. Commer. Res 20(3): 233.
MJ Liberatore (1982) Book review of the analytic hierarchy process: Planning, priority setting, resource allocation by Thomas l. saaty. American Journal of Mathematical and Management Sciences 2: 165-172.
-

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.




